Category Archives: medicine

Bromadiolone toxicokinetics: diagnosis and treatment implications

Bromadiolone Poisoning Treatment: Vitamin K1, INR Monitoring and Emergency Management

Bromadiolone poisoning is an important cause of potentially severe and prolonged bleeding because bromadiolone is a long-acting anticoagulant rodenticide (LAAR), commonly called a superwarfarin. It inhibits vitamin K recycling and consequently reduces the activity of vitamin K–dependent coagulation factors II, VII, IX and X.

Unlike ordinary warfarin exposure, bromadiolone poisoning may produce prolonged coagulopathy lasting weeks to months, and patients may require prolonged treatment with vitamin K1 (phytomenadione) and repeated INR monitoring.

Clinical pearl: A patient can appear clinically well initially and subsequently develop severe coagulopathy. A normal INR early after exposure does not necessarily exclude clinically important toxicity.


What is Bromadiolone?

Bromadiolone is a second-generation 4-hydroxycoumarin anticoagulant rodenticide. It belongs to the long-acting anticoagulant rodenticide group along with compounds such as brodifacoum and difenacoum.

It is considerably more persistent than conventional warfarin and can produce prolonged suppression of vitamin K–dependent coagulation.

Mechanism of bromadiolone poisoning

Bromadiolone inhibits vitamin K epoxide reductase, preventing regeneration of active vitamin K.

This results in impaired γ-carboxylation and activation of:

  • Factor II
  • Factor VII
  • Factor IX
  • Factor X
  • Protein C
  • Protein S

The result is progressive impairment of coagulation and an increased risk of spontaneous or trauma-related bleeding.


Clinical Features of Bromadiolone Poisoning

Patients may initially have no symptoms.

As coagulopathy develops, manifestations may include:

  • Epistaxis
  • Gingival bleeding
  • Easy bruising
  • Hematuria
  • Hematemesis
  • Melena
  • Hematochezia
  • Menorrhagia
  • Intramuscular bleeding
  • Hemarthrosis
  • Retroperitoneal bleeding
  • Intracranial hemorrhage
  • Hemoperitoneum
  • Severe anemia
  • Hemorrhagic shock

Intracranial hemorrhage is an uncommon but potentially life-threatening complication.


Initial Assessment

Management begins with stabilization and assessment of bleeding risk.

ABCDE assessment

A — Airway

Assess airway protection, particularly in patients with:

  • Altered consciousness
  • Intracranial hemorrhage
  • Massive upper gastrointestinal bleeding

B — Breathing

Assess:

  • Respiratory rate
  • Oxygen saturation
  • Respiratory distress

C — Circulation

Assess:

  • Heart rate
  • Blood pressure
  • Peripheral perfusion
  • Capillary refill
  • Evidence of active bleeding
  • Shock

Establish IV access and obtain blood samples early.

D — Disability

Assess:

  • Glasgow Coma Scale
  • Pupils
  • Focal neurological deficits
  • Headache
  • Seizures

Consider intracranial hemorrhage when neurological symptoms occur in a patient with severe coagulopathy.

E — Exposure

Look carefully for:

  • Bruising
  • Petechiae
  • Hematomas
  • Hematuria
  • Gastrointestinal bleeding
  • Injection or trauma sites

Investigations in Bromadiolone Poisoning

Important investigations include:

Essential tests

  • PT/INR
  • aPTT
  • CBC with platelet count
  • Hemoglobin/hematocrit
  • Blood group and crossmatch
  • Fibrinogen
  • Renal function
  • Liver function tests
  • Serum electrolytes

Additional tests when indicated

  • Factor II, VII, IX and X levels
  • Mixing study
  • Specific bromadiolone/superwarfarin assay
  • CT brain for neurological symptoms
  • Ultrasound/CT for suspected internal bleeding

Bromadiolone poisoning characteristically produces a vitamin K–dependent factor deficiency pattern, particularly involving factors II, VII, IX and X.


Bromadiolone Poisoning Treatment

The two major principles of treatment are:

  1. Replace vitamin K1 to overcome the anticoagulant effect
  2. Rapidly replace deficient coagulation factors when there is significant or life-threatening bleeding

1. Vitamin K1 — The Specific Antidote

Vitamin K1 (phytomenadione/phytonadione) is the cornerstone of treatment.

It restores the availability of reduced vitamin K and allows synthesis of functional vitamin K–dependent clotting factors.

Importantly, vitamin K does not immediately replace circulating clotting factors. Therefore, a patient with life-threatening hemorrhage may require coagulation-factor replacement in addition to vitamin K.

Route of vitamin K1

Depending on severity:

  • Oral vitamin K1 — useful for stable patients and prolonged treatment
  • IV vitamin K1 — preferred when rapid treatment is required or oral administration is not feasible

IV vitamin K should be administered cautiously because serious hypersensitivity/anaphylactoid reactions have been reported.


Vitamin K1 Dose in Bromadiolone Poisoning

There is no universally standardized dose or duration for bromadiolone poisoning.

The required dose depends on:

  • INR
  • Severity of coagulopathy
  • Presence or absence of bleeding
  • Amount/type of rodenticide exposure
  • Response to treatment
  • Recurrence of coagulopathy after dose reduction or interruption

Published cases have used a wide range of regimens, including repeated IV vitamin K followed by high-dose oral vitamin K.

For severe superwarfarin poisoning, high-dose vitamin K1 administered repeatedly throughout the day may be necessary, with dosing adjusted according to the INR and clinical response. Some toxicology literature reports doses as high as 50–100 mg/day or more in severe cases, but these doses should be individualized with toxicology/hematology guidance rather than applied as a routine dose.

Important

Do not use a single fixed vitamin K dose for every bromadiolone ingestion.

The appropriate regimen should be guided by:

Clinical bleeding + INR/PT response + toxicology consultation


2. Management of Active or Life-Threatening Bleeding

Vitamin K alone may be insufficient initially because the liver requires time to synthesize new coagulation factors.

For patients with major, life-threatening bleeding, rapid coagulation-factor replacement is required.

Options include:

4-factor PCC

4-factor prothrombin complex concentrate (PCC) provides factors:

  • II
  • VII
  • IX
  • X

and can rapidly correct severe vitamin K antagonist–associated coagulopathy.

Fresh Frozen Plasma

FFP can also replace deficient coagulation factors.

It may be used when PCC is unavailable or according to local protocol.

Packed RBCs

Packed red blood cells should be administered when significant blood loss has caused clinically important anemia or hemorrhagic shock.

The choice and dose of blood products should be individualized according to bleeding severity, hemoglobin, hemodynamic status and local transfusion protocols.

Key principle

Major bleeding = vitamin K1 + rapid coagulation-factor replacement + definitive control of the bleeding source.


3. Control the Source of Bleeding

Correction of coagulopathy is not enough if active bleeding continues.

Depending on the site, management may include:

  • Endoscopic hemostasis
  • Surgical intervention
  • Interventional radiology
  • Neurosurgical intervention
  • Local pressure
  • Gynecological intervention
  • Management of gastrointestinal bleeding

A published case of severe bromadiolone-associated intracranial/other hemorrhage illustrates the need for both correction of coagulopathy and definitive treatment of the bleeding source.


4. Activated Charcoal and Gastric Decontamination

Routine gastrointestinal decontamination is not the main treatment for established bromadiolone poisoning.

Evidence summarized in toxicology reviews indicates that multiple-dose activated charcoal has not demonstrated reliable benefit for superwarfarin poisoning.

Any consideration of activated charcoal after a recent ingestion should therefore be individualized according to:

  • Time since ingestion
  • Amount ingested
  • Airway protection
  • Toxicology advice
  • Product formulation

Do not delay resuscitation or treatment of hemorrhage for gastrointestinal decontamination.


5. INR Monitoring

INR is the most practical laboratory marker for monitoring the anticoagulant effect.

A patient with significant exposure should have serial:

  • PT/INR
  • aPTT
  • CBC
  • Hemoglobin

The frequency depends on the severity of poisoning and treatment response.

In severe poisoning, INR may need to be checked frequently during initial stabilization, followed by less frequent monitoring once a stable vitamin K regimen has been established.


Why Long-Term Treatment May Be Necessary

This is one of the most important differences between bromadiolone and ordinary warfarin poisoning.

Bromadiolone is highly lipophilic and has prolonged persistence in the body. Human pharmacokinetic data demonstrate a prolonged terminal elimination phase; one clinical study estimated a terminal half-life of approximately 24 days.

Therefore:

Stopping vitamin K too early → recurrent INR elevation → recurrent bleeding.

Cases have documented recurrence of severe coagulopathy after vitamin K was discontinued despite an initially normal INR.


When Can Vitamin K Be Stopped?

There is no universally accepted evidence-based stopping rule for bromadiolone poisoning.

A normal INR while the patient is receiving vitamin K does not necessarily mean that bromadiolone has been eliminated.

A commonly used approach is:

  1. Stabilize the INR with vitamin K.
  2. Continue vitamin K while the toxic effect persists.
  3. Gradually reduce/taper treatment when appropriate.
  4. Stop vitamin K under specialist supervision.
  5. Recheck PT/INR approximately 48–72 hours after stopping vitamin K.
  6. Restart treatment if significant coagulopathy recurs.

Where available, quantitative serum bromadiolone/superwarfarin testing can provide additional information, although there is no universally validated concentration threshold that independently determines when treatment can safely stop.


Bromadiolone Poisoning: Practical Treatment Algorithm

Suspected bromadiolone ingestion

↓

Assess ABCDE + bleeding

↓

Obtain PT/INR ± aPTT, CBC and other baseline investigations

↓

Is there major/life-threatening bleeding?

YES

→ Vitamin K1
→ 4-factor PCC or FFP for rapid factor replacement
→ RBC transfusion when indicated
→ Definitive control of bleeding
→ Serial INR monitoring
→ Toxicology/hematology consultation

NO

→ Assess exposure and coagulation profile
→ Serial PT/INR monitoring
→ Vitamin K1 when clinically indicated
→ Continue monitoring because delayed/prolonged coagulopathy can occur

↓

INR controlled?

YES

→ Continue appropriately dosed vitamin K1
→ Regular INR monitoring
→ Gradual reduction when appropriate

NO

→ Check adherence
→ Reassess ongoing exposure/re-exposure
→ Increase/adjust vitamin K under specialist guidance
→ Evaluate for ongoing bleeding

↓

Considering stopping vitamin K?

→ Stop only after adequate clinical assessment
→ Recheck INR after approximately 48–72 hours
→ Restart treatment if coagulopathy recurs


Bromadiolone Poisoning in Children

Children may accidentally ingest rodenticide bait.

A child who has ingested a small amount may remain asymptomatic, but the risk assessment depends on:

  • Exact product
  • Active ingredient
  • Concentration
  • Amount ingested
  • Child’s weight
  • Time since ingestion
  • Repeated versus single exposure

Do not automatically assume that every rodenticide product contains bromadiolone. The product label should be checked whenever possible.

For children with suspected anticoagulant rodenticide exposure, consultation with a poison center or medical toxicologist is recommended.


Important Differential Diagnoses

A markedly prolonged PT/INR should not automatically be attributed to bromadiolone.

Consider:

  • Warfarin exposure
  • Other anticoagulant rodenticides
  • Vitamin K deficiency
  • Liver disease
  • Disseminated intravascular coagulation
  • Acquired factor inhibitors
  • Congenital coagulation-factor deficiencies
  • Malabsorption
  • Drug interactions

Superwarfarin poisoning should particularly be considered in a patient with unexplained prolonged PT/INR and bleeding, especially when the history is unclear.


Key Differences: Warfarin vs Bromadiolone

FeatureWarfarinBromadiolone
UseTherapeutic anticoagulantRodenticide
ClassVitamin K antagonistLong-acting vitamin K antagonist
Common nameWarfarinSuperwarfarin
Duration of effectUsually shorterProlonged
CoagulopathyUsually manageable over daysMay persist weeks–months
AntidoteVitamin K1Vitamin K1
Severe bleedingFactor replacement may be requiredFactor replacement may be required
Long-term vitamin KSometimesFrequently required in severe poisoning
MonitoringINRSerial INR/PT

Important Clinical Pearls

1. A normal early INR does not completely exclude toxicity.

The anticoagulant effect can be delayed because existing circulating clotting factors must first decline.

2. Vitamin K1 is the specific treatment.

Bromadiolone poisoning is fundamentally a vitamin K antagonist poisoning.

3. Vitamin K does not immediately correct major hemorrhage.

In life-threatening bleeding, rapidly replace coagulation factors with 4-factor PCC or FFP, according to availability and local protocol.

4. Treatment may last for months.

Severe bromadiolone poisoning can require prolonged vitamin K1 therapy because of its long persistence.

5. Do not stop vitamin K simply because the INR becomes normal.

The INR may normalize because of administered vitamin K while the rodenticide remains in the body.

6. Monitor after stopping therapy.

A recurrence of INR elevation after vitamin K withdrawal strongly suggests persistent anticoagulant activity.

7. Always identify the active ingredient.

“Rat poison” is not a diagnosis. Different rodenticides have different toxic mechanisms and treatments.


Summary

Bromadiolone poisoning is a potentially life-threatening superwarfarin poisoning characterized by prolonged vitamin K–dependent coagulopathy.

The cornerstone of treatment is:

Vitamin K1 + INR-guided monitoring + rapid factor replacement when significant bleeding is present.

Patients with severe poisoning may require high-dose and prolonged vitamin K1 therapy for weeks or months. Treatment should not be discontinued solely because the INR has normalized while the patient is receiving vitamin K. After vitamin K is eventually stopped, repeat coagulation testing after approximately 48–72 hours can help identify recurrent anticoagulation.

Because bromadiolone poisoning can be prolonged and potentially fatal, significant exposures, abnormal coagulation studies, or any active bleeding warrant urgent medical evaluation and specialist toxicology/hematology input.


Frequently Asked Questions

What is the antidote for bromadiolone poisoning?

Vitamin K1 (phytomenadione/phytonadione) is the specific antidote for bromadiolone-induced vitamin K antagonism.

How long does bromadiolone poisoning last?

Severe poisoning can persist for weeks to months, reflecting the prolonged persistence of bromadiolone and its anticoagulant effect.

Does bromadiolone poisoning cause bleeding?

Yes. Severe poisoning can cause epistaxis, gum bleeding, hematuria, gastrointestinal bleeding, internal hemorrhage and, rarely, intracranial hemorrhage.

Can bromadiolone poisoning be treated?

Yes. Early recognition, vitamin K1 therapy, appropriate coagulation-factor replacement and close monitoring can successfully reverse the coagulopathy.

Is vitamin K enough for severe bleeding?

Not necessarily. Vitamin K restores coagulation factor production but does not provide an immediate supply of functional factors. Patients with life-threatening bleeding may require 4-factor PCC or FFP in addition to vitamin K1.

Can bromadiolone poisoning recur after treatment?

Yes. Recurrent coagulopathy can occur after vitamin K is stopped because bromadiolone may remain active in the body for a prolonged period.


SEO Keywords

Primary keyword:
Bromadiolone poisoning treatment

Secondary keywords:

  • Bromadiolone poisoning
  • Bromadiolone treatment
  • Bromadiolone antidote
  • Vitamin K for bromadiolone poisoning
  • Bromadiolone toxicity
  • Bromadiolone overdose
  • Bromadiolone rodenticide poisoning
  • Superwarfarin poisoning treatment
  • Anticoagulant rodenticide poisoning
  • Vitamin K1 treatment
  • Bromadiolone INR
  • Bromadiolone coagulopathy
  • Rat poison poisoning treatment
  • Rodenticide poisoning treatment
  • Bromadiolone bleeding
  • Bromadiolone poisoning management

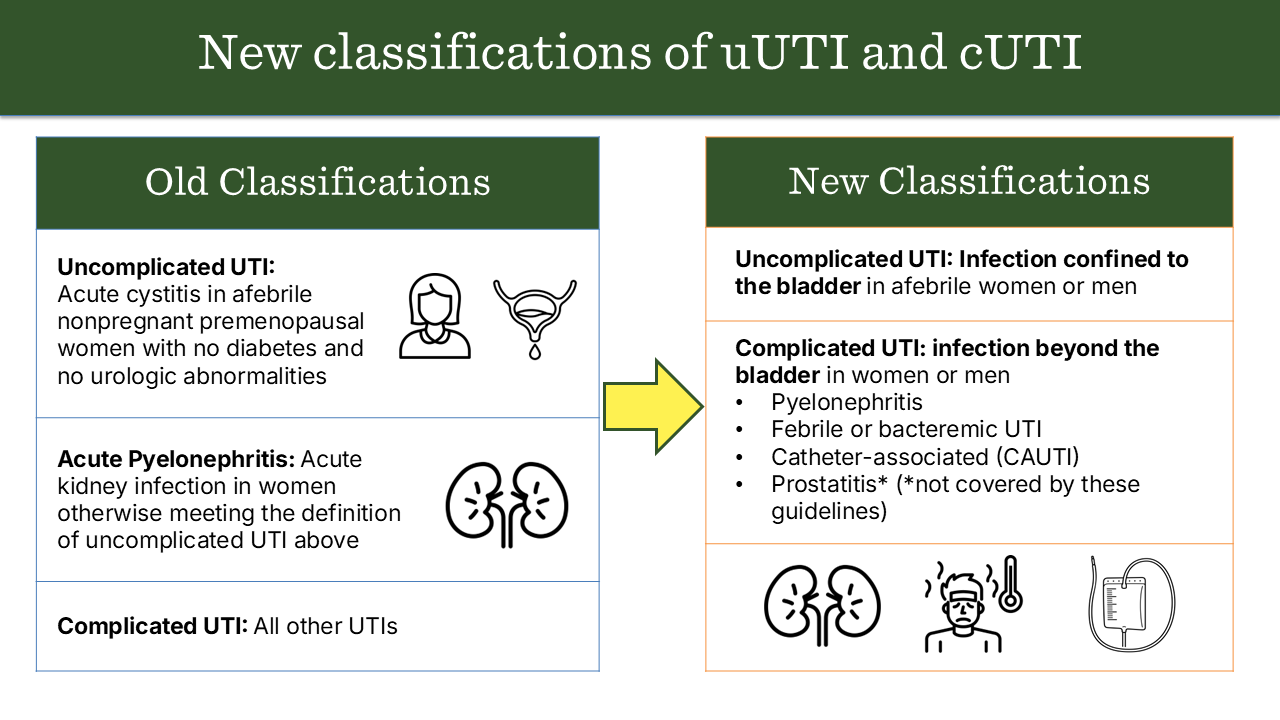
Complicated Vs Uncomplicated UTI (Notes) – Clinical Practice and Diagnosis


1. Definition

TypeDefinition
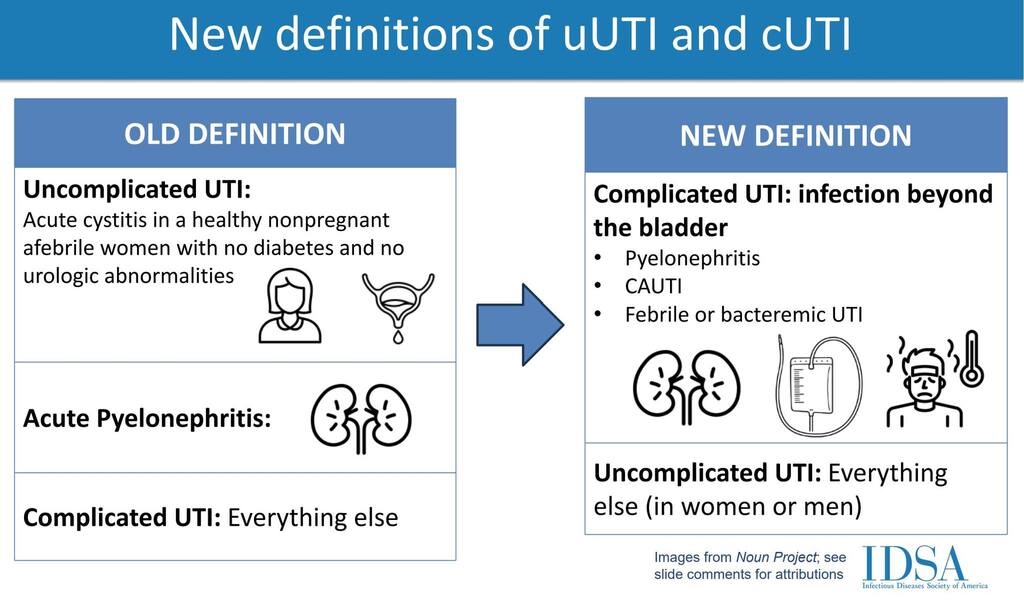
Uncomplicated UTIInfection of the lower urinary tract (bladder and urethra) occurring in an otherwise healthy, non-pregnant woman with a structurally and functionally normal urinary tract.
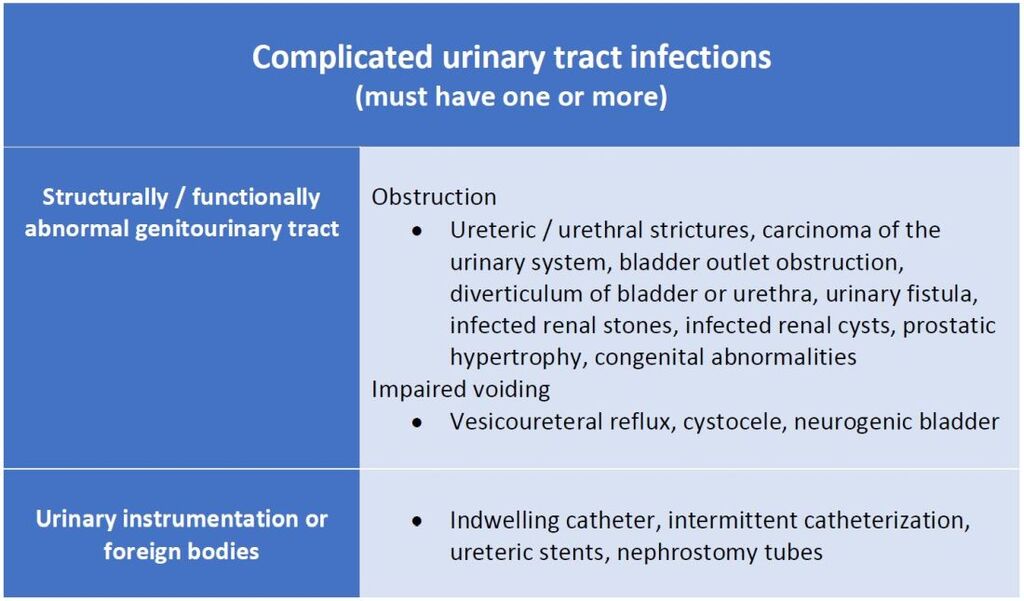
Complicated UTIUTI occurring in individuals with structural or functional abnormalities of the urinary tract, comorbidities, or other risk factors that increase risk of treatment failure or recurrence.

2. Typical Patients

TypeCommon in
UncomplicatedHealthy, premenopausal, non-pregnant females
ComplicatedMales, pregnant females, children, elderly, diabetics, catheterized patients, immunocompromised patients

3. Etiology

TypeCommon PathogensSpecial Pathogens
UncomplicatedE. coli (≈80–90%), Staphylococcus saprophyticusRarely Klebsiella, Proteus
ComplicatedE. coli, Klebsiella, Proteus, Enterobacter, Pseudomonas, Enterococcus, CandidaOften multidrug-resistant (MDR) organisms

4. Predisposing / Risk Factors

Uncomplicated:

  • Female gender (short urethra)
  • Sexual activity
  • Spermicides

Complicated:

  • Structural: Stones, strictures, obstruction (BPH, vesicoureteral reflux)
  • Functional: Neurogenic bladder, indwelling catheter
  • Systemic: Diabetes mellitus, immunosuppression
  • Male gender
  • Pregnancy

5. Clinical Presentation

TypeFeatures
UncomplicatedDysuria, frequency, urgency, suprapubic pain, no systemic signs
ComplicatedMay have fever, chills, flank pain, systemic toxicity, sepsis, poor response to therapy

6. Investigations

TypeLab Approach
UncomplicatedUrinalysis ± urine culture (often empirical treatment)
ComplicatedUrine culture mandatory, imaging (USG, CT KUB) if obstruction suspected, blood cultures if febrile

7. Treatment

TypeApproach
UncomplicatedShort-course oral antibiotics (3–5 days): Nitrofurantoin, TMP-SMX, Fosfomycin, Pivmecillinam
ComplicatedLonger course (7–14 days), guided by culture; IV therapy if severe (Ceftriaxone, Piperacillin-tazobactam, Carbapenems for MDR); treat underlying cause (remove catheter, relieve obstruction)

8. Prognosis

TypePrognosis
UncomplicatedExcellent, low recurrence with proper hygiene
ComplicatedRisk of recurrence, sepsis, renal scarring, abscess

9. Example Cases

ScenarioType
25-year-old woman with dysuria, no comorbiditiesUncomplicated
60-year-old diabetic man with fever, flank painComplicated
Pregnant woman with bacteriuriaComplicated
Patient with indwelling Foley catheter and feverComplicated

Summary Table

FeatureUncomplicatedComplicated
HostHealthy femaleAny comorbidity or abnormality
SiteLower UTI (cystitis)Any (cystitis, pyelonephritis, sepsis)
OrganismsUsually E. coliPolymicrobial, resistant organisms
TherapyShort courseLong course, guided by culture
PrognosisExcellentVariable, risk of recurrence

Approach to a Child with Wheeze

1. Definition

  • Wheeze is a high-pitched, musical, continuous sound produced by airflow through narrowed airways, typically during expiration.
  • Indicates airway obstruction at any level (from trachea to small bronchi).

2. Initial Assessment

A. ABC Assessment

  • Airway: Ensure patency; look for obstruction (secretions, foreign body).
  • Breathing:
    • Respiratory rate, effort (retractions, nasal flaring, grunting)
    • Oxygen saturation (SpO₂)
    • Presence and distribution of wheeze
    • Work of breathing (mild / moderate / severe)
  • Circulation: Heart rate, capillary refill time, BP, color.

B. Severity Assessment

SeverityFeatures
MildSpeaking in sentences, SpO₂ > 94%, mild wheeze
ModerateBreathless, feeding difficulty, SpO₂ 90–94%
SevereCannot talk/feed, SpO₂ < 90%, exhaustion, cyanosis, silent chest

3. Focused History

AspectKey Points
Onset & CourseSudden (foreign body) vs gradual (infection/asthma)
Frequency/PatternRecurrent vs first episode
TriggersViral infection, allergen, exercise, cold air, smoke
Associated SymptomsFever, cough, coryza, vomiting, feeding difficulty
Past Medical HistoryPrevious wheezing, atopy, eczema, prematurity, GERD
Family/Social HistoryAsthma, allergies, smoking, housing
Drug historyRecent medications, response to bronchodilators

4. Physical Examination

  • General: Distress, cyanosis, growth, hydration.
  • Respiratory system:
    • Chest expansion, use of accessory muscles
    • Percussion (hyperresonant / dull)
    • Auscultation:
      • Wheeze: polyphonic (asthma/viral), monophonic (focal obstruction)
      • Air entry: symmetrical or reduced
      • Crackles: suggest infection or bronchiolitis
  • Cardiac: Murmurs (congenital lesions)
  • Other systems: Skin (eczema), ENT (allergic rhinitis), clubbing.

5. Differential Diagnosis

Age GroupCommon Causes
Infant (<1 yr)Bronchiolitis, congenital airway anomalies, aspiration, GERD
Toddler (1–5 yr)Viral-induced wheeze, foreign body aspiration, asthma
Older child (>5 yr)Asthma, allergic bronchitis, chronic suppurative lung disease

6. Investigations

(Usually guided by clinical picture; many cases diagnosed clinically)

  • Pulse oximetry – essential.
  • Chest X-ray – if first episode, focal findings, suspicion of foreign body/pneumonia.
  • Blood tests – if severe or infection suspected.
  • Allergy testing / IgE – in recurrent or atopic cases.
  • Spirometry / Peak Flow – for older cooperative children (asthma diagnosis).
  • Bronchoscopy – if persistent localized wheeze or suspicion of foreign body.

7. Management

A. Immediate Management

  • Mild/Moderate:
    • Nebulized or inhaled salbutamol (via spacer or nebulizer)
    • Oxygen if SpO₂ < 94%
    • Oral prednisolone if known asthma or recurrent wheeze
  • Severe / Life-threatening:
    • High-flow oxygen
    • Nebulized salbutamol ± ipratropium bromide
    • IV steroids (hydrocortisone)
    • IV magnesium sulfate / aminophylline / salbutamol if poor response
    • Consider PICU referral

B. Underlying Cause

  • Bronchiolitis – supportive (O₂, fluids, suction)
  • Foreign body – urgent ENT/pulmonary referral
  • Asthma – follow stepwise management (as per BTS/SIGN or GINA)

8. Long-term Management

  • Identify triggers and educate parents on avoidance.
  • Asthma education: inhaler technique, action plan.
  • Follow-up to reassess control and adjust therapy.

9. Red Flags

  • Silent chest, exhaustion, cyanosis
  • Poor air entry or asymmetry
  • Persistent localized wheeze
  • Failure to thrive or recurrent pneumonia
  • Sudden onset without infection (→ foreign body)

10. Summary Table

StepKey Action
1ABC and severity assessment
2Focused history
3Physical examination
4Consider differential diagnoses
5Targeted investigations
6Manage acutely + treat cause
7Educate and follow-up

What is freeze indicator in vaccine? A guide


1. Definition

A Freeze Indicator is a device or label used to detect whether a vaccine (or other temperature-sensitive product) has been exposed to temperatures at or below its freezing point—usually 0°C or lower.

  • Purpose: To prevent use of vaccines that have lost potency or safety due to freezing.
  • Target vaccines: Mainly freeze-sensitive vaccines containing aluminum adjuvant (e.g., DTP, Pentavalent, Hep B, HPV), which lose potency irreversibly when frozen.

2. Types of Freeze Indicators

TypeFunctionExample Devices
Single-use chemical indicatorsChange color irreversibly after exposure to freezing temperature for a certain durationFreeze-tag®
Electronic data loggersRecord continuous temperature; can be set to trigger an alarm if freezing occursLogTag®, ELPRO
Phase-change indicatorsContain material that solidifies/melts at 0°C, showing visible changeSome cold chain box indicators

3. Working Principle

  • Based on phase change of a material or thermochemical reaction triggered by freezing temperatures.
  • The change is irreversible, serving as a permanent record of freezing exposure.

4. Interpretation (Using Freeze-tag® example)

  • OK: Indicator window shows ✓ (no freezing exposure).
  • ALARM / ❌: Indicator window shows a cross mark (freezing detected).
  • Device cannot be reset—once tripped, the product must be considered potentially damaged.

5. Pediatric Relevance – Vaccines Affected by Freezing

  • DTP / DT / Td
  • Pentavalent
  • Hepatitis B
  • HPV
  • Pneumococcal conjugate vaccine (PCV)
  • Inactivated polio vaccine (IPV)
  • Hib (liquid formulations)

Freeze-stable vaccines (e.g., OPV, measles, BCG before reconstitution) are not affected by freezing.


6. Field Handling Notes

  • Always check freeze indicator + VVM before using a vaccine.
  • Avoid placing freeze-sensitive vaccines in direct contact with ice packs.
  • In outreach, use conditioned ice packs (sweating surface, internal ice still solid).
  • If freeze indicator shows alarm → vaccine should be discarded as per national guidelines.

7. Limitations

  • Some indicators respond only to certain freezing durations (e.g., >60 min below 0°C).
  • Cannot detect multiple freeze–thaw cycles unless electronic logger is used.
  • Doesn’t measure heat exposure—must be paired with VVM for complete cold chain safety.

If you want, I can make you a side-by-side pediatric cold chain safety chart comparing VVMs vs Freeze Indicators with examples, WHO limits, and affected vaccines so it’s all in one quick-reference sheet.
Would you like me to prepare that?

FMGE Exam: All You Need to Know in 2024 and Beyond

The FMGE exam, or Foreign Medical Graduate Examination, is an essential stepping stone for international medical graduates (IMGs) who wish to practice medicine in India. Conducted by the National Board of Examinations (NBE), this examination assesses the medical knowledge of foreign-trained doctors, ensuring that they meet the standards required to deliver healthcare in the country.

What is FMGE?

The FMGE full form is Foreign Medical Graduate Examination. It is a mandatory exam for all medical professionals who have completed their medical degrees from universities outside India. After passing the FMGE exam, candidates are granted a provisional or permanent registration with the National Medical Commission (NMC), which is required to practice medicine in India.

Importance of FMGE Exam

The FMGE exam holds great significance as it bridges the gap between the medical education received overseas and the practical medical standards in India. It ensures that foreign medical graduates meet the necessary skillset and knowledge before treating patients in Indian hospitals and clinics.

FMGE Exam Date 2024

For those preparing for the FMGE exam date 2024, it is essential to stay updated with the official announcements. The FMGE exam date is announced by the National Board of Examinations (NBE), typically around 2-3 months before the exam takes place. In 2024, the FMGE exam date will be scheduled for specific months, so candidates must frequently check the NBE website for the most accurate and up-to-date information.

FMGE Result 2024

The FMGE result 2024 will be made available a few weeks after the exam date. The results can be checked on the official NBE website, and it’s important to note that the FMGE result is issued in the form of a scorecard. Candidates who successfully pass the exam will be eligible to apply for the FMGE admit card in the following years.

How to Download the FMGE Admit Card

The FMGE admit card is a crucial document for appearing in the FMGE exam. Once you have registered and applied for the exam, you can download the FMGE admit card from the official NBE website. The FMGE admit card contains important details such as your exam date, exam center, and personal information. It is essential to keep the admit card safe and carry it with you to the exam center.

FMGE Result 2025 and Beyond

As we look ahead, the FMGE result 2025 will be crucial for many who are aspiring to work in India after completing their medical education abroad. The format of the exam and result declaration is expected to stay consistent. FMGE result 2025 will follow the same timeline, and candidates will need to keep track of any updates released by NBE.

NBE FMGE: What You Need to Know

The NBE FMGE is a well-structured exam that follows a set pattern, which includes multiple-choice questions (MCQs) that assess the candidate’s medical knowledge and understanding of various subjects. It is vital for candidates to be well-prepared and familiar with the exam format before appearing. Moreover, the NBE is known for its efficient conduct of exams, ensuring fairness and accuracy in results.

Important Dates: FMGE Exam and Admit Card

The FMGE exam date 2025 will be announced by the NBE well in advance. Once you know the FMGE exam date, you will have enough time to prepare thoroughly. It is also essential to keep track of the FMGE admit card 2025 release date. The admit card is typically available a few weeks before the exam, and candidates must download it promptly to avoid any last-minute confusion.

How to Prepare for FMGE Exam

Preparation for the FMGE exam requires strategic planning and dedication. While some candidates might find it easier, others may need additional time and effort. Here’s a breakdown of a few steps that can help in preparation:

  1. Understand the FMGE Syllabus: Start by reviewing the syllabus for the FMGE exam to know which subjects and topics you will be tested on.
  2. Practice with Previous Papers: Solve past FMGE exam papers to familiarize yourself with the question format and time constraints.
  3. Join Online Coaching or Study Groups: You can also sign up for online FMGE preparatory courses or study groups for extra support and guidance.
  4. Stay Updated with Important Announcements: Check the NBE website regularly for updates regarding FMGE exam date, FMGE admit card, and other essential details.

Conclusion

The FMGE exam is a critical examination for medical professionals who have completed their medical degree from foreign universities. Whether you are preparing for the FMGE exam date 2024 or looking ahead to the FMGE exam date 2025, staying informed and prepared is the key to success. With the right resources and commitment, passing the FMGE exam can open doors to a rewarding career in the Indian medical field.

Remember to monitor the official website for the most accurate and up-to-date information regarding the FMGE result, FMGE admit card, and FMGE exam dates. Stay focused on your preparation, and good luck with your exam!

50 MCQs on Diploma in Pharmacy License Examination for Nepal Pharmacy Council

The Diploma in Pharmacy (D. Pharm) License Examination is an essential test for pharmacy graduates seeking to obtain a professional license. Below are 50 multiple-choice questions (MCQs) covering various aspects of pharmacy practice, pharmacology, pharmaceutics, and regulations.


Section 1: Pharmaceutical Chemistry & Pharmacology

  1. Which of the following is an example of an alkaloid? a) Aspirin
    b) Atropine
    c) Paracetamol
    d) Ibuprofen
  2. The first-pass metabolism primarily occurs in the: a) Liver
    b) Kidney
    c) Lungs
    d) Stomach
  3. Which of the following drugs is classified as an NSAID? a) Omeprazole
    b) Diclofenac
    c) Diazepam
    d) Insulin
  4. The therapeutic index (TI) of a drug is a measure of its: a) Potency
    b) Safety
    c) Solubility
    d) Absorption
  5. The antidote for organophosphate poisoning is: a) Atropine
    b) Naloxone
    c) Vitamin K
    d) Protamine sulfate
  6. Penicillins act by inhibiting: a) RNA synthesis
    b) DNA replication
    c) Cell wall synthesis
    d) Protein synthesis
  7. Which of the following is a beta-blocker? a) Amlodipine
    b) Metoprolol
    c) Furosemide
    d) Digoxin
  8. The primary site of action of loop diuretics is: a) Proximal tubule
    b) Loop of Henle
    c) Distal tubule
    d) Collecting duct
  9. Warfarin is monitored by measuring: a) Platelet count
    b) Prothrombin time (PT/INR)
    c) Activated partial thromboplastin time (aPTT)
    d) Hemoglobin levels
  10. The neurotransmitter primarily involved in Parkinson’s disease is: a) Dopamine
    b) Serotonin
    c) GABA
    d) Acetylcholine

Section 2: Pharmaceutics & Drug Formulation

  1. The disintegration test is performed to evaluate: a) Tablet hardness
    b) Drug solubility
    c) Drug release time
    d) Stability
  2. The major advantage of enteric-coated tablets is: a) Faster absorption
    b) Protection from gastric acid
    c) Better solubility
    d) Extended shelf-life
  3. The bioavailability of a drug refers to: a) Its dissolution rate
    b) The proportion that reaches systemic circulation
    c) Its metabolism
    d) Its elimination half-life
  4. Emulsions are stabilized by: a) Preservatives
    b) Buffers
    c) Surfactants
    d) Chelating agents
  5. The most commonly used lubricant in tablet formulation is: a) Magnesium stearate
    b) Starch
    c) Talc
    d) Lactose

Section 3: Pharmacy Law & Ethics

  1. The Drugs and Cosmetics Act, 1940 regulates: a) Drug pricing
    b) Manufacture, sale, and distribution of drugs
    c) Patent rights
    d) Health insurance policies
  2. The schedule under the Drugs and Cosmetics Act that deals with prescription drugs is: a) Schedule H
    b) Schedule X
    c) Schedule M
    d) Schedule P
  3. A pharmacist’s primary duty is to: a) Sell maximum medicines
    b) Ensure proper drug use and patient safety
    c) Promote a specific brand
    d) Increase pharmacy profits
  4. The Good Manufacturing Practices (GMP) are outlined in: a) Schedule T
    b) Schedule M
    c) Schedule Y
    d) Schedule Z
  5. Which of the following is a Schedule X drug? a) Amoxicillin
    b) Morphine
    c) Paracetamol
    d) Cetirizine

Section 4: Hospital & Clinical Pharmacy

  1. The term ‘adverse drug reaction’ (ADR) refers to: a) A predictable side effect
    b) An unintended harmful reaction
    c) A drug overdose
    d) A placebo effect
  2. The WHO Model List of Essential Medicines is updated every: a) 2 years
    b) 5 years
    c) 10 years
    d) Annually
  3. The primary function of a hospital formulary is to: a) List available drugs in the hospital
    b) Control drug pricing
    c) Recommend pharmaceutical marketing strategies
    d) Promote generic drugs only
  4. Drug interactions occur when: a) Two drugs are taken together and affect each other’s activity
    b) A patient develops an allergy
    c) A drug expires
    d) A drug is taken on an empty stomach
  5. Pharmacovigilance refers to: a) Monitoring drug safety and adverse reactions
    b) Developing new drugs
    c) Improving drug packaging
    d) Controlling pharmaceutical sales

These MCQs cover essential topics required for the Diploma in Pharmacy License Examination. Preparing with such questions enhances knowledge and improves chances of success. For better results, practice regularly and stay updated with the latest developments in pharmacy laws and clinical guidelines.

Answer Key for 50 MCQs on Diploma in Pharmacy License Examination

  1. b) Atropine
  2. a) Liver
  3. b) Diclofenac
  4. b) Safety
  5. a) Atropine
  6. c) Cell wall synthesis
  7. b) Metoprolol
  8. b) Loop of Henle
  9. b) Prothrombin time (PT/INR)
  10. a) Dopamine
  11. c) Drug release time
  12. b) Protection from gastric acid
  13. b) The proportion that reaches systemic circulation
  14. c) Surfactants
  15. a) Magnesium stearate
  16. b) Manufacture, sale, and distribution of drugs
  17. a) Schedule H
  18. b) Ensure proper drug use and patient safety
  19. b) Schedule M
  20. b) Morphine
  21. c) Pharmacokinetics
  22. d) Tetracycline
  23. a) Buccal route
  24. b) Volume of distribution
  25. c) 6 months
  26. a) Schedule C
  27. d) Paracetamol
  28. b) Increased drug stability
  29. a) Half-life
  30. c) Phase I and Phase II reactions
  31. b) An increase in drug concentration
  32. d) All of the above
  33. a) Albumin
  34. c) Tablets
  35. d) International Nonproprietary Name (INN)
  36. b) Pharmacovigilance
  37. c) Drug interactions
  38. a) Increased absorption of drugs
  39. b) 1st January 1947
  40. c) Decreased plasma protein binding
  41. b) Pharmacodynamics
  42. d) Dissolution rate
  43. a) Therapeutic drug monitoring
  44. b) Subcutaneous injection
  45. c) Sodium chloride
  46. d) Phase IV (Post-marketing surveillance)
  47. a) Rectal route
  48. c) First-order kinetics
  49. b) Relative bioavailability
  50. a) 0.9% Sodium chloride